NewNMC’s advertising guidelines for doctors are in force from 6 Oct 2026. See what to change, and get a free compliance auditNew NMC advertising rules for doctors: what to change
Paid Ads

Performance Max for Healthcare Lead Generation: When to Use It and When to Switch It Off

Performance Max usually looks excellent in Google Ads and mediocre in the appointment book. The controls that exist, the conversion definition that fixes it, and the honest test for whether to keep it.

Performance Max for Healthcare Lead Generation: When to Use It and When to Switch It Off

Performance Max usually looks excellent in the Google Ads interface and mediocre in the appointment book. That gap is the whole subject of this article.

The cost per lead comes down. The lead volume goes up. Then the front desk starts reporting that half the calls are people asking about a service you do not offer, in a city you do not serve, and the consultant wants to know why the theatre list has not moved.

Nothing has malfunctioned. The campaign did precisely what it was told. It was told the wrong thing.

It optimises to the conversion you give it

Performance Max is a bidding system pointed at a goal. Whatever event you mark as the primary conversion becomes the definition of success, and the system will get extremely good at producing that event as cheaply as possible.

Give it a form submission, and it will find people who submit forms. Some of them want surgery. Many of them want a price list, a second opinion by email, or a job.

In a specialty where the gap between an enquiry and a patient is small — a dental check-up, a walk-in clinic, a diagnostic test — this barely matters. In a specialty where the gap is large and expensive — IVF, oncology, joint replacement, bariatrics — it is the difference between a campaign that funds the department and one that quietly drains it.

This is not a Performance Max flaw. It is the same flaw in every automated bidding strategy. It is simply more visible here, because the automation has more freedom.

Where it genuinely works in healthcare

Multi-location groups with real budget and wide geography. The consolidation is the point: one campaign covering search, YouTube, Display, Discover, Gmail and Maps inventory, across forty locations, without forty campaign structures to maintain.

Services with broad consumer demand and a clear online action. Dental hygiene, eye tests, health check packages, vaccination, diagnostics. High volume, short decision, a booking that completes online.

Markets where you already have search covered and want the remaining inventory. Performance Max is a reasonable way to buy the long tail around an account that is already working, and the broad-reach services above are where that long tail actually exists.

Where it fails

A single-location clinic with a small monthly budget. The system needs conversion volume to learn from, and a campaign producing a handful of conversions a month never leaves the learning phase — it just spends.

High-value, low-volume procedures. There is not enough signal, and the signal that exists arrives weeks after the click.

Any account where brand search is a large share of conversions. Performance Max will happily serve against your own brand terms, claim the conversion, and report a wonderful cost per acquisition built on traffic you were getting for free. If you are not excluding brand, your reported improvement may be entirely an accounting artefact.

And any account where nobody is willing to look at lead quality. If the only number reviewed at the monthly meeting is cost per lead, this campaign type will win that meeting every time while losing the business. That is the failure pattern behind most of the poor lead quality work we get called into.

The controls you actually have

The "black box" complaint is several years out of date. The controls are real, and most healthcare accounts use none of them.

Campaign-level negative keywords, self-serve, up to ten thousand per campaign. Use them. In healthcare the standing list is long before you even start: "free", "jobs", "salary", "course", "government", competitor names, insurance schemes you do not accept, and every adjacent condition you do not treat.

Brand lists from the Shared Library, applied as brand exclusions, so the campaign stops buying your own name. Note that these apply to Search and Shopping inventory, and that a newly submitted brand takes several weeks to become available — so do this before you launch, not after the first bad month. If you want brand traffic, buy it in a search campaign where you can see it.

Search themes, which tell the system what you want rather than restricting what it does. Treat them as steering, not targeting.

Asset group structure. One asset group per service line, with its own headlines, images, video and landing page, is the difference between a campaign that respects your service mix and one that averages it.

Location targeting set to presence, not presence-or-interest. The default setting will show your Gurugram clinic to people in another state researching Gurugram.

Reporting has improved too. There is an aggregated search terms view — less detail than a search campaign gives you, but enough to build a negative list from. And channel performance reporting, which Google rolled out on 30 April 2025, breaks spend and conversions out across Search, YouTube, Discover, Gmail, Maps, Display and search partners. If your last opinion of Performance Max was formed in 2022, check what your account exposes now before repeating it.

What you still cannot do reliably is confine the campaign to chosen channels. There has been limited testing of channel opt-outs, but it is not a generally available control, and you should plan on the assumption that your budget will go wherever the system sends it.
Want this applied to your practice? Get a free paid ads audit.

Book my free audit

Conversion hygiene is the entire fix

Everything above is secondary to this.

Define the primary conversion as the outcome you actually want, as far down the funnel as you can measure. For most practices that is a booked appointment that the patient attended, not a form fill.

That means offline conversion import: the CRM sends the qualified and attended appointments back to Google Ads, with the click identifier attached, so the bidding learns from real patients rather than from form-fillers. It is a week of setup and it changes what the system optimises towards more than any other single change.

Demote everything else to secondary. Form fills, calls under thirty seconds, brochure downloads — record them, do not bid on them.

Two cautions. First, do not send patient-identifying information to an ad platform. Google does not sign a business associate agreement, so for a US covered entity no protected health information may reach it; in India, the Digital Personal Data Protection Act, 2023 and the Digital Personal Data Protection Rules, 2025 govern what you may do with enquiry data and require purpose-specific consent. What goes back is a click identifier and a conversion value, not a diagnosis.

Second, respect the lag. If your average time from click to attended appointment is five weeks, a campaign judged at thirty days is being judged before its results exist.

The policy layer

Google's Healthcare and medicines policy restricts a range of treatment advertising, varies by country, and requires certification and third-party verification for some categories — prescription medicines, online pharmacies and telemedicine among them, verified through LegitScript in most markets. Check your specialty against the current policy rather than against what was allowed last year.

The policy that catches more healthcare accounts by surprise is the separate one on personalised advertising. Google treats health as a sensitive category, and for health-related content it disallows advertiser-curated audiences, Customer Match, your own data segments, audience expansion and lookalike-style targeting. Google's predefined audiences — in-market, affinity, demographics, location — remain available, with restrictions.

That has a direct consequence for Performance Max. Audience signals built from a patient list are the first thing most agencies reach for, and in a health context that is exactly the input the policy rules out. Build the signal from Google's own predefined audiences and from the asset group's landing page instead, and put the effort into conversion quality rather than audience craft.

It is also one more reason asset groups should be organised around services rather than around patient conditions. The service framing is clearer to the system and further from the policy line. The full position for clinics is in our Google Ads healthcare guide.

Performance Max or Demand Gen

They answer different questions, and accounts often buy the wrong one.

Performance Max is for capturing demand across every inventory type at once, optimised to a conversion. It is a consolidation tool.

Demand Gen is for creating demand on YouTube, Discover and Gmail, with creative control and audience control that Performance Max does not give you. If the objective is that people in your city learn a service exists, that is a Demand Gen brief, and measuring it on cost per lead will make it look like a failure.

Running both and comparing them on the same metric is the most common way to reach the wrong conclusion about either.

Run it as an experiment, and be willing to switch it off

The diagnostic that settles the argument:

Keep a properly structured search campaign running on treatment-intent terms. Launch Performance Max alongside it, with brand excluded, negatives applied, asset groups per service, and the primary conversion set to an attended appointment. Give it a defined window — long enough to clear the conversion lag, which in most specialties means eight to twelve weeks.

Then compare on cost per attended patient and on revenue per patient, not on cost per lead. Ask the front desk what the calls were like.

If it wins, scale it. If it does not, switch it off. The willingness to do the second part is what separates accounts that use this campaign type well from accounts that have simply been running it since someone turned it on.

What to do first

  1. Add brand exclusions. Today, before anything else.
  2. Build the negative keyword list from your last ninety days of enquiry notes.
  3. Split asset groups by service line, each with its own landing page.
  4. Set up offline conversion import so an attended appointment is the primary conversion.
  5. Set location targeting to presence.
  6. Set a review date far enough out to survive the lag, and put cost per attended patient on the agenda.

If you would rather have someone run that sequence with you, that is the bulk of what our healthcare PPC work consists of in the first month.

---

If you want an outside read on whether Performance Max is earning its budget in your account — including whether it is buying your own brand and what the leads actually became — get a free audit and we will send the findings whether or not you work with us. Or book a strategy call.

Filed underperformance max lead generationperformance max healthcareperformance max vs demand generationgoogle ads healthcare policypmax for clinics

About the author

Founder & CEO · Gurugram, India

Nishu founded Branding Pioneers in 2016 with one rule that hasn't changed since: healthcare only. She'd run digital strategy at a top-10 Indian agency and watched generalist marketing underserve medical clients who needed something built for how patients actually search and decide. So she left to build the specialist instead. It's now an 80-person team working with healthcare brands worldwide.

Free guide · 17 pages

The Patient Acquisition Blueprint

A 90-day plan from first search to booked appointment.

The Pioneers Brief — one essay, three benchmarks, one teardown, every Thursday. Subscribe free →

Related guide: Google Ads Playbook for Healthcare

Free paid ads audit

Your next chapter starts with a conversation.

Three quick questions. We come prepared with a plan for your specialty and city.

  • A 30-minute call with a healthcare specialist
  • Your top three growth opportunities, in writing
  • Honest advice — even if that means not hiring us
  • No obligation and no hard sell
You’ll speak with a senior strategist
Consultations are hosted by Arush Thapar’s team.
Step 1 of 3Takes 30 seconds

What do you want to improve first?

Details stay privateNo obligationReply within 1 working day

Performance from the portfolio

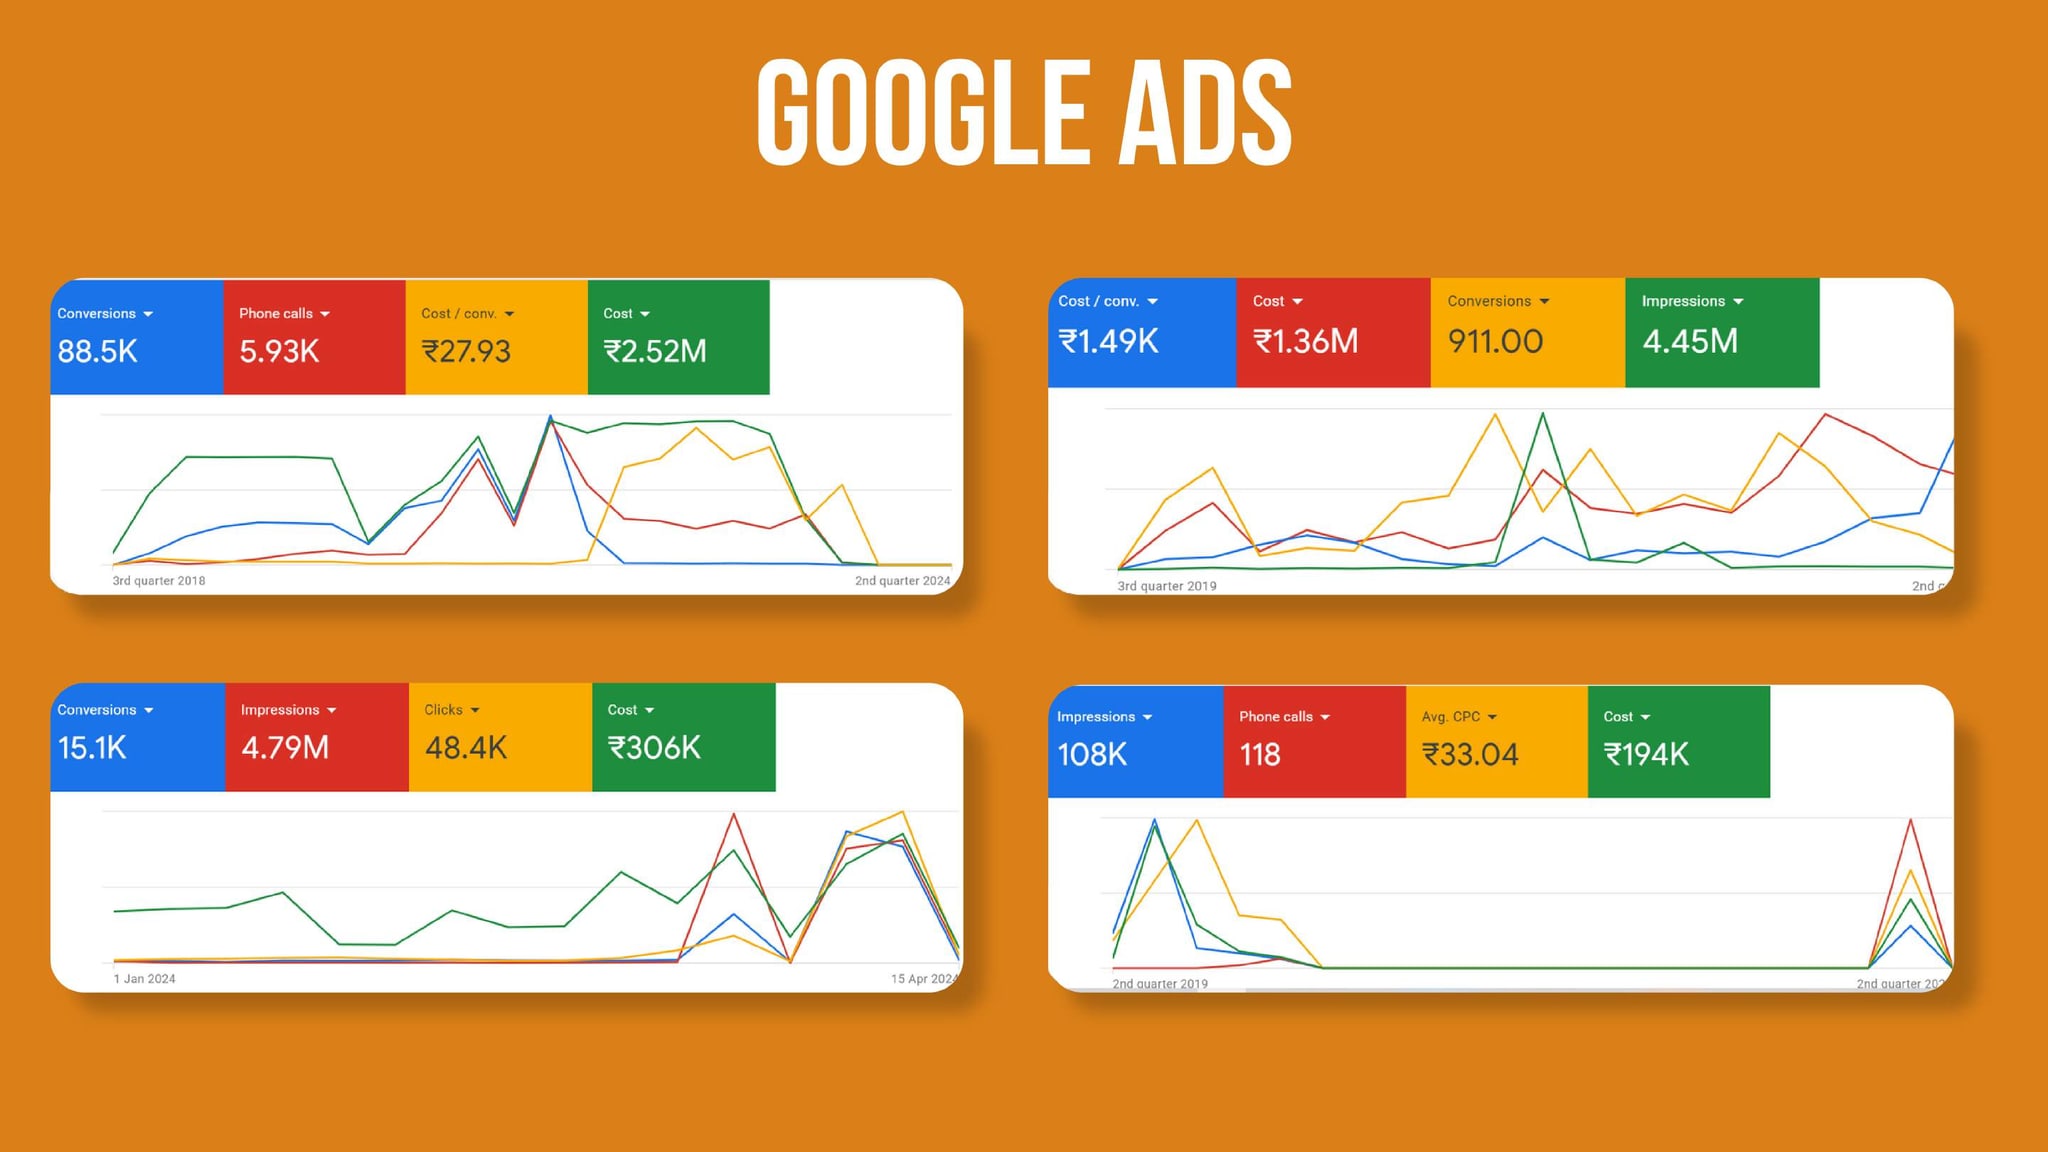
48.4K clicks, with spend and conversions in view.

An existing campaign snapshot shows recorded conversion actions alongside traffic, visibility and advertising spend.

Clicks
48.4K
Recorded conversion actions
15.1K
Advertising spend
₹306K
Google Ads · Original portfolio1 January–15 April 2024 · lower-left account snapshot
Original Google Ads portfolio; lower-left January to April 2024 report shows 48.4K clicks, 4.79M impressions, 15.1K conversions and 306K rupees in spend.
Figures are from the lower-left snapshot only; the other panels show separate reports. Account identity and conversion definitions are not supplied. Conversion actions are not confirmed patients or bookings. No prior-period comparison is available in this capture.

performance max healthcare lead generation · Portfolio

Paid advertising: selected work

Explore the collection →